


Navigating the intricate world of healthcare requires a compass, a roadmap guiding clinicians toward the most effective and evidence-based practices. Clinical practice guidelines (CPGs) serve as this crucial navigational tool, offering synthesized recommendations intended to optimize patient care. However, behind the seemingly straightforward pronouncements of these guidelines lie a set of “hidden rules” – unspoken principles that govern their creation, interpretation, and application. Understanding these underlying precepts is crucial for both healthcare providers seeking to implement best practices and for patients aiming to make informed decisions about their health.
The first hidden rule is the principle of Evidence Hierarchies and Grading Systems. Clinical guidelines aren’t built on whimsy; they are grounded in rigorous scientific inquiry. Yet, not all evidence is created equal. A meticulously conducted randomized controlled trial (RCT) typically carries more weight than an observational study or expert opinion. To codify this disparity, most guidelines employ hierarchical systems, such as the GRADE (Grading of Recommendations Assessment, Development and Evaluation) approach. GRADE categorizes evidence based on study design, risk of bias, consistency, directness, and precision. This structured evaluation allows readers to discern the strength of the evidence supporting each recommendation. It’s vital to recognize that a “strong” recommendation doesn’t necessarily mean a guaranteed outcome, but rather reflects the confidence in the overall body of evidence.
Closely linked to evidence grading is the concept of Recommendation Strength. Guidelines often use standardized language to indicate the strength of a recommendation. Terms like “strong recommendation” or “recommend with high certainty” suggest that the benefits of the intervention outweigh the harms and burdens, and that most patients would likely desire the recommended course of action. Conversely, a “weak recommendation” or “conditional recommendation” implies a more nuanced balance, where the benefits and harms are less clear-cut, and individual patient preferences play a greater role. This gradation in recommendation strength acknowledges the heterogeneity of patient populations and the inherent uncertainty in clinical decision-making.

A third, less explicit, rule revolves around Contextual Applicability. Guidelines are not designed to be applied in a vacuum. The context in which care is delivered – including available resources, local expertise, and patient-specific factors – profoundly influences the appropriateness of a given recommendation. For example, a guideline recommending a sophisticated diagnostic test may be impractical in a resource-limited setting. Similarly, a treatment strategy effective for one patient population might be inappropriate for another with significant comorbidities or cultural considerations. Thus, clinicians must exercise sound clinical judgment, tailoring guideline recommendations to the individual patient and their unique circumstances.
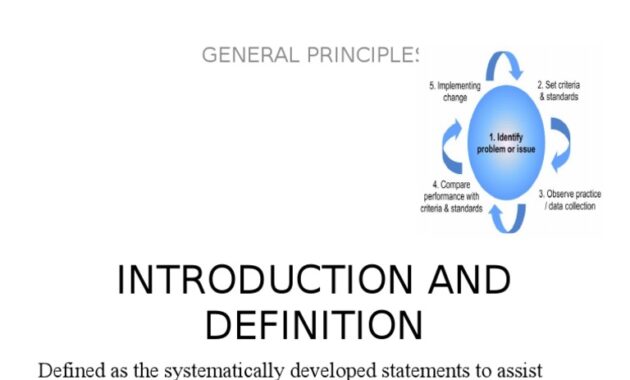
The fourth hidden rule addresses Implementation Strategies and Barriers. Formulating a guideline is only half the battle; effective implementation is paramount. Guidelines often implicitly assume that clinicians possess the necessary knowledge, skills, and resources to enact the recommended practices. However, this is not always the case. Successful guideline implementation necessitates a multifaceted approach, encompassing education and training, workflow redesign, and the establishment of robust audit and feedback mechanisms. Overcoming potential barriers, such as resistance to change, lack of time, or inadequate infrastructure, is critical for translating evidence into practice.
Moving on to another critical aspect is the understanding of Potential Conflicts of Interest. The development of clinical guidelines can be influenced by various factors, including financial relationships with pharmaceutical companies, personal biases, and institutional affiliations. To maintain transparency and objectivity, guideline developers should disclose any potential conflicts of interest. Readers should critically evaluate guidelines, considering the potential influence of these conflicts on the recommendations. A guideline free from conflicts of interest inspires greater confidence in its validity and impartiality.
Furthermore, the concept of Dynamic Updating and Revision Cycles should be understood. The medical landscape is constantly evolving, with new research emerging at a rapid pace. Guidelines are not static documents; they require periodic updates and revisions to reflect the latest evidence. Most guideline developers establish a predetermined review cycle, typically every three to five years, to ensure that recommendations remain current and evidence-based. Clinicians should be aware of the publication date and review the most recent version of a guideline to avoid relying on outdated information. A failure to update can lead to stagnation and suboptimal patient care.
Another subtle rule is the principle of Patient Values and Preferences Integration. Guidelines often emphasize the importance of shared decision-making, where patients actively participate in choosing the most appropriate course of treatment. This involves eliciting patient values, preferences, and goals, and incorporating them into the decision-making process. A guideline recommendation, even a strong one, should not be imposed on a patient without their informed consent. Respecting patient autonomy and promoting shared decision-making fosters trust and enhances patient satisfaction.
Finally, it’s essential to acknowledge the Limitations and Unanswered Questions. Even the most rigorously developed guidelines have limitations. They may not address every possible clinical scenario, and they may be based on incomplete or conflicting evidence. Guidelines should explicitly acknowledge these limitations and identify areas where further research is needed. This transparency allows clinicians to exercise caution when applying guidelines to complex or atypical cases and encourages ongoing inquiry to refine clinical practice.
In conclusion, clinical practice guidelines represent a cornerstone of evidence-based medicine. By deciphering the hidden rules that govern their creation and application, healthcare professionals can leverage these tools to deliver high-quality, patient-centered care. The journey toward optimal patient outcomes demands a discerning understanding of evidence hierarchies, recommendation strength, contextual applicability, implementation strategies, conflict of interest, dynamic updating, patient values, and inherent limitations. Only then can we truly unlock the transformative potential of clinical guidelines in the pursuit of healthcare excellence.




